Regulators and lawmakers are considering proposed changes to CLIA and PAMA involving medical laboratory services
Clinical laboratories and pathology groups should monitor a series of federal regulatory developments underway this fall. The proposals and documents will potentially affect how lab managers and staff do their jobs and how much Medicare reimbursement medical laboratories receive for certain diagnostic tests next year.
Among the initiatives under consideration are the following:
Below are details about these laboratory-related federal bills and regulatory documents that observant laboratory managers will want to track in the coming months.
“Clinical laboratories need to make sure that they have proper requisitions and documentation for genetic testing that involves telemedicine.” Danielle Tangorre, JD (above), a partner at law firm Robinson and Cole LLP in Albany, NY, told Dark Daily. (Photo copyright: Robinson and Cole LLP.)
CLIA Fee Increases and Testing Personnel Changes
The federal Centers for Medicare and Medicaid Services (CMS) is examining fee and personnel changes for CLIA. Officials from CMS are reviewing public comments on the proposal ahead of publishing a final rule.
Among other changes, the proposal would:
Institute a 20% across-the-board increase on existing fees.
Establish a biennial increase of CLIA fees for follow-up surveys, substantiated complaint surveys, and revised certificates.
Add doctoral, master’s, and bachelor’s degrees in nursing to qualify testing personnel for high and moderate complexity testing.
“The Practitioner does not have sufficient contact with or information from the purported patient to meaningfully assess the medical necessity of the items or services ordered or prescribed.
“The Telemedicine Company compensates the Practitioner based on the volume of items or services ordered or prescribed, which may be characterized to the Practitioner as compensation based on the number of purported medical records that the Practitioner reviewed.
“The Telemedicine Company only furnishes items and services to Federal health care program beneficiaries and does not accept insurance from any other payor.
“The Telemedicine Company does not expect Practitioners (or another Practitioner) to follow up with purported patients nor does it provide Practitioners with the information required to follow up with purported patients (e.g., the Telemedicine Company does not require Practitioners to discuss genetic testing results with each purported patient).”
And more.
“In the telehealth space, the issue the OIG has flagged is that genetic tests are being ordered without patient interaction or with only brief telephonic conversations,” Danielle Tangorre, JD, a partner at law firm Robinson & Cole LLP in Albany, N.Y., told Dark Daily.
New Bill May Eliminate 2023 Medical Laboratory Payment Cuts Under PAMA
Medical labs and pathology groups face payment cuts of up to 15% for 800 lab tests on the Medicare Clinical Lab Fee Schedule (CLFS) on Jan. 1, 2023, as part of PAMA.
The bill proposes to move regulatory oversight of LDTs from CLIA to the federal Food and Drug Administration (FDA). Champions of the bill argue that FDA regulation is needed for in vitro clinical tests (IVCTs) because they are similar to medical devices and bring with them patient safety concerns.
The bill seemed ready for a Senate vote over the summer but stalled. On Sept. 30, Congress passed a short-term resolution to keep the federal government funded. During negotiation, the VALID Act was removed from the larger spending package, according to Boston law firm Ropes and Gray.
Expect discussion to renew in Congress about the VALID Act after the mid-term elections.
Clinical laboratory leaders and pathology group managers will want to closely monitor the progress of these four federal legislative and regulatory developments. Each of the possible actions described above would significantly change the status quo in the compliance requirements and reimbursement arrangements for both clinical laboratory testing and anatomic pathology services.
Potentially increasing the revenue write-off burden for clinical laboratories, HRSA changes, insurance contracting, policy and coverage questions for genetic and genomic testing, and patient relationship disconnects will expose cracks in lab test claim generation and billing processes
Last year it was estimated that collection agencies held $140 billion in unpaid medical bills, in addition to the amount of unpaid bills in pre-collection status, according to a New York Times report. More recently, the American Hospital Association showed that hospitals have provided upwards of $700 billion in uncompensated care since 2000, with over $40 billion in 2019 alone.
Because strategies to collect the unpaid can be complicated and time-consuming, many healthcare organizations, including clinical laboratories, choose to write off these uncollectible bills. Dark Daily and The Dark Report have covered clinical laboratory revenue challenges for many years. In considering the paths forward, software-as-a-service (SaaS) provider FrontRunner Healthcare (FrontRunnerHC) recently provided snapshots into the how and where of improved collections.
Fixing Data Issues that Lead to Forfeited Clinical Laboratory Revenue
The underpinnings of unpaid lab tests are many. In a recent interview with Dark Daily, FrontRunnerHC CEO and Founder John (JD) Donnelly estimated that about one-third of claims (prior to submission) include incorrect or missing patient information, such as insurance policy identification or demographics. These gaps undermine an organization’s ability to get paid. Donnelly estimates that bad-debt write-offs for commercial payer claims average over 15% of charges. To address these challenges, the company’s clean claims SaaS provides “instantaneous” patient insurance, demographic, and financial information.
Whether lower-dollar accessions such as routine testing, or the higher-dollar accessions of genetic tests, uncollected payments add up. Donnelly said that, in 2021, almost one-third of the company’s clients uncovered revenue ranging from $1 million to over $90 million using the software. Donnelly also estimated that the return for clients averages eight times the value of the investment in using the automated solution.
In one example, Sonora Quest, a joint venture between Banner Health and Quest Diagnostics, reported a 10-15% decline in write-offs due to aged claims, a savings of over $1million annually, as published in a case study. “As an aside, in a presentation at the Executive War College last November, they also attributed improvements in patient satisfaction measures to the software, including a 65% decrease in abandoned calls, 28% improvement in their call service factor, and 19% decrease in patient call volumes,” stated Donnelly.
Questions About Cost of Care Likely Cause Stress for Patients
As many know, nonpay issues are problematic not only for lab businesses and anatomic pathology practices but also for patients and their families who have little predictability with their cost of care in the midst of stressful health events. “From the time a patient is registered to the time the claim is paid, there are more challenges than people realize that jeopardize the patient’s experience as well as the provider’s ability to get reimbursed,” Donnelly explained. Medical laboratory administrators have struggled to respond, often by using traditional manual methods such as call centers, or more recently by considering the use of data automation tools.
From the patient payment perspective, Donnelly said, a good strategy is having the ability, on demand, to understand each patient’s specific financial situation and likelihood to pay. For example, using FrontRunnerHC’s software to gauge patients’ propensity to pay and determine financial disposition strategies, lab administrators may choose to offer payment plans or hardship discounts to those falling under the federal poverty level (FPL). Or they may choose to send a collection agency only the past-due accounts for patients who have a low likelihood to pay rather than sending them all past due accounts and focus in-house efforts on the others. One genetics lab client who recently started leveraging these software capabilities “is already seeing more than 5% in incremental net collections,” according to Donnelly.
Further, an estimated 2 million people switch insurance plans each month, reported Axios. “That velocity of change is tough for providers to manage, but it’s critical as insurance eligibility and registration issues are the number one reason for claims denials,” Donnelly said.
For a sense of the magnitude of the problem, “Between 25 and 33 cents of every dollar you spend on medical care pays for health care’s back office,” wrote Dana Miller Ervin in September 2021 for a series of investigations called “The Price We Pay,” published at WFAE 90.7 news in Charlotte, North Carolina. “Every medical provider and laboratory in the country has to negotiate with insurance companies. And since there are 900 health insurers, 6,000 hospitals and more than 100,000 physician practices—many of which are independent of larger systems—there are hundreds of thousands of negotiations.”
New Clinical Laboratory Business Challenges Making News Now
All these issues affecting revenue cycle management (RCM) for independent clinical laboratories, hospital and health system laboratories, and physician office laboratories could be compounded by three emerging issues.
Donnelly said that many lab clients have yet to be reimbursed for COVID tests they have performed, despite their HRSA-required due diligence prior to submitting the claims before the deadline. To avoid additional reimbursement risk, many labs have made the decision to stop testing the uninsured or charge them for it, ABC News reported in late March. As of early April, however, Congress was in discussions to re-fund at least some of the Uninsured Program, reported Politico.
Secondly, and also daunting, are the questions surrounding payer coverage and reimbursement for genetic tests and genomic testing. Thanks to high-deductible health plans (HDHPs), clinical laboratories and anatomic pathology groups increasingly must collect deductibles that may be the full amount of the test – and directly from patients rather than from insurance companies. Therefore, there is more demand from patients to understand their expected cost before the test, Donnelly added.
Problems can arise, for both labs and patients, if they don’t know whether a test has been preauthorized for medical necessity or if they lack accurate insurance information such as in-network or out-of-network. “Getting all the needed and accurate info upfront prior to it going into the LIS [Laboratory Information System] can be a reimbursement game changer,” stated Donnelly.
“For a high complexity, high-throughput diagnostic lab, an efficient workflow is critical,” stated Kyle Koeppler, President of nuCARE Medical Solutions Inc., a FrontRunnerHC client. “Capturing the correct patient demographics and insurance information at patient intake increases the accuracy of every order and makes every process involving patient information much more efficient,” Koeppler shared. “It’s simply too costly to risk having inaccurate information at intake.”
And lest we forget, the Protecting Access to Medicare Act (PAMA) is looming with its reimbursement cuts planned through 2026, and requirements of many labs to report private payer rates on a test-by-test basis. While delayed again, the 2023 PAMA reporting requirements and payment cuts must not be ignored, and planning is needed in order to ensure appropriate reimbursement, Donnelly added.
Addressing Long Payment Cycles for Claims, Dead Ends, and Decreased Collection Rates
The CAQH report cites that data automation resulted in efficiency savings of $122 billion annually for the US healthcare system in 2020 yet “meaningful opportunities for additional savings remain.”
Data automation can reduce the burden of labor-intensive functions in coding, billing, filing appeals, and collecting from payers and patients and, therefore, reduce overall RCM costs. The Council for Affordable Quality Healthcare’s (CAQH) 2020 Index reported, “Considering the millions of times these transactions occur every day, the savings potential across the healthcare economy [from streamlining administrative processes] is significant.”
“One way to avoid potential write-offs is by reworking a claim, but the rework is often left undone,” stated John (JD) Donnelly (above), CEO and Founder of FrontRunnerHC. “The better way to avoid a potential write-off is to ensure you’ve got a clean claim in the first place.” (Photo copyright: FrontRunnerHC.)
The intended outcome is an increase in the total amount of revenue collected from the same number of claims.
To that end, FrontRunnerHC’s software links critical data within its partner ecosystem. This ecosystem includes the well-established credit reporting agencies as well as data available through connected healthcare payers and providers equipped with electronic data interchange (EDI) capabilities. “While an employee may be able to manually work about six accessions in an hour, clients can process approximately 40,000 patients in an hour through software automation, leaving staff to work on more value-added initiatives,” stated Donnelly.
Ideally, missing and inaccurate patient information or insurance verification, which are crucial for producing prompt payments and clean claims, should be corrected before a specimen is collected, Donnelly said. However, if the laboratory is nursing aging accounts receivable (AR), Donnelly advises an audit and cleanup of the AR backlog as a first step to quickly fix information errors and reduce write-offs. “In your AR bucket of $10 million, you may have $3 million that’s collectible or $9.8 million that’s collectible. By leveraging software to clean up what can be collected, clients can go after the money they deserve.”
Improve Collections Through Data Automation While Assisting in the Patient Financial Journey
With the rise of telehealth/telemedicine, healthcare consumerism, and care delivered to nontraditional sites, it makes sense that the idea of the clinical laboratory as a silent partner in healthcare could be changing.
“Could we one day see patients asked for not only their preferred pharmacy but their preferred clinical laboratory as well?” Donnelly pondered and added, “I think the answer is yes, and it’s sooner than many think.”
Understanding the patient’s experience is a key step in providing patient-centered care. Therefore, patient experience programs that originate at clinical laboratories where specimens are processed, but before specimens have been collected, could make these labs more visible in their markets and enable them to capitalize on the advantages of data automation to sustainably improve revenue cycle management.
“The patient’s financial journey which runs in parallel to their clinical journey can get pretty bumpy, and those bumps impact their overall experience as well as the provider’s bottom line,” added Donnelly. “Getting accurate patient information upfront and catching any changes to the information as needed throughout the process helps clients create a smoother patient journey by enabling them to quickly manage through the bumps or eliminate them altogether.”
—Liz Carey
This article was produced in collaboration with FrontRunnerHC.
Limited availability of COVID-19 clinical lab tests is major topic at federal briefings and news stories, yet many of nation’s labs are laying off staff and at point of closing
Cash flow at the nation’s clinical laboratories has crashed, with revenues down by more than $5 billion since early March. This is the biggest financial disaster for the nation’s clinical laboratory industry in its 100-year history and it couldn’t come at a worse time for the American public and the US healthcare system.
At the precise moment when the nation needs clinical laboratories to begin performing millions of tests for SARS-CoV-2, the coronavirus that causes the COVID-19 illness, those same labs are watching their cash flow collapse.
Data from multiple sources gathered by The Dark Report, sister publication of Dark Daily, confirm that—beginning in early March and continuing through last week—clinical laboratories in the United States saw incoming flows of routine specimens decline by between 50% and 60%. During this same time, lab revenue fell by similar amounts.
Clinical Lab Industry Currently Losing $800 to $900 Million Weekly
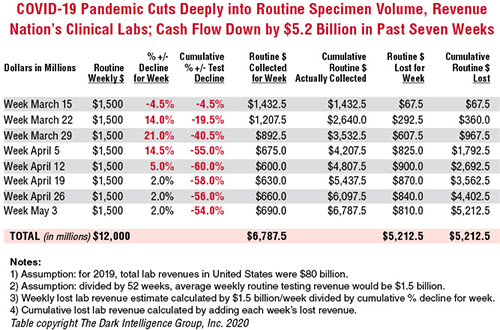
To give this decline context, the healthcare system spends about $80 billion annually on medical laboratory testing. Thus, labs across the US generated about $1.5 billion in revenue each week during 2019 and into 2020. By April 5, the decline in routine lab specimen volumes reached 55% to 60%. Since then, the clinical lab industry now loses between $800 million and $900 million each week. Total revenue loss from previous levels is already estimated to be $5.2 billion, and it is growing by an additional $800 million to $900 million every week that patients stay away from hospitals and physicians’ offices.
In the eight weeks since the COVID-19 pandemic caused patients to cease coming to hospitals and visiting their doctors, incoming routine specimens and revenue fell by 60%, causing cumulative lost routine revenue of $5.2 billion for the clinical laboratory industry in the United States. Each week that the existing shelter-in-place directives are effective, labs lose another $800 million to $900 million. The Dark Report based these estimates on data provided by multiple companies working with lab billing/claims, middleware analytical solutions, and customer relationship management (CRM) and electronic health record (EHR) products. (Chart copyright: The Dark Intelligence Group, Inc.)
The recent dire financial condition of labs small and large has gone unremarked by federal healthcare officials at the daily White House COVID-19 Task Force briefings. National news sources have yet to report on this development and its implications for successfully expanding the availability and numbers of COVID-19 tests in response to the pandemic.
The rapid and deep decline in specimens and revenue is not limited to clinical laboratories. Biopsy cases referred to anatomic pathology groups have declined by 50% to 60%. Some subspecialty pathology labs saw case referrals drop by 80% or more.
The nation’s two biggest clinical laboratory companies confirmed similar declines in their normal daily flow of routine specimens. Both companies recently reported first-quarter earnings (which included the month of March).
Quest Diagnostics, LabCorp Each Disclose Volume Declines of 50% to 60%
During its Q1 2020 earnings conference call, Chairman, President, and CEO of Quest Diagnostics (NYSE:DGX), Steve Rusckowski, stated, “In April, volume declines continue to intensify as we are seeing signs that volume declines are bottoming out at around 50% to 60%.”
The drop-off in routine lab test referrals was the similar at LabCorp (NYSE:LH). “In our diagnostics business, at the end of the quarter, we experienced reductions in demand for testing of 50% to 55% versus the company’s normal daily levels,” explained Glenn Eisenberg, Executive Vice President and CFO during LabCorp’s Q1 2020 earnings call. “This reduction in demand impacted testing volume broadly but was more heavily weighted towards routine procedures.”
Interviews with independent clinical lab owners and the administrative directors of hospital and health system labs further confirm this rapid and dramatic decline in the number of routine specimens arriving in their labs. Fewer specimens mean fewer claims, which means less revenue to laboratories.
Two Different Financial Futures for ‘Have’ Labs and ‘Have Not’ Labs
What happens next to the clinical laboratory industry in the United States—and to its ability to continue ramping up the availability of adequate numbers of COVID-19 tests in major cities, small towns, and rural areas—will be a story of “haves” and “have nots.”
The “haves” are clinical labs that have access to money. These are publicly-traded lab companies, academic medical center labs, and the sophisticated labs of health networks that operate multiple hospitals. In each case, these organizations have capital reserves and access to loans that will probably enable them to sustain COVID-19 lab testing services at the large volumes required to respond to the pandemic.
clinical labs operated by community hospitals and rural hospitals that were not financially robust before the onset of the pandemic; and,
specialty lab companies that perform a specific number of proprietary diagnostic tests (and for which demand has collapsed as patients stopped seeing their doctors).
Medicare Led Payers in the ‘Lab Test Price Race to the Bottom’
Prior to the onset of the SARS-CoV-2 pandemic, the finances of the “have-not” labs were already shaky, with many on the verge of filing bankruptcy, closing, or selling to a bigger lab company. Much blame for the deteriorating finances at a large proportion of community lab companies, community hospital labs, and rural hospital labs can be attributed to the deep, multi-year price cuts to the Medicare Part B clinical laboratory fee schedule as mandated by the Protecting Access to Medicare Act of 2014 (PAMA).
Medicare’s multi-year cuts to lab test prices were immediately copied by most state Medicaid programs. During this period, private payers followed Medicare’s lead and enacted their own deep cuts to the prices they paid labs for both routine tests and molecular/genetic tests.
That is why—when the pandemic intensified in early March—the 50% to 60% drop in specimens and revenue that hit these labs starved them of essential cash flow. When polled, the owners and directors of these labs acknowledge layoffs of the majority of their staff in all departments. They also reported substantial delays—both in submitted lab test claims and in getting payment for those claims—because claims-processing departments at the labs and private health insurers are understaffed due to shelter-in-place directives.
COVID-19 Test Revenue Helps Only Labs Performing Those Tests
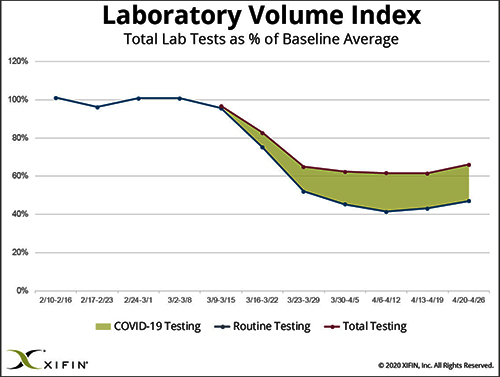
Revenue from COVID-19 testing is helping certain labs offset the revenue loss from fewer routine specimens. XIFIN, Inc., a San Diego company that provides revenue cycle management (RCM) services for clinical laboratories and pathology groups, analyzed the lab test claims for COVID-19 rapid molecular tests. It determined that labs performing these tests are generating enough revenue from these test claims to equal about 20% of their pre-pandemic revenue.
The chart above was prepared by XIFIN, Inc., of San Diego and is based on the changes XIFIN observed in the volume of routine clinical laboratory test claims generated by client labs on a weekly basis. In the first two months of 2020, routine lab test claims ran at expected levels until the first week of March. During the rest of March, routine lab test claims declined by 60%. During April, incoming routine lab test claims remained 55% to 60% below pre-pandemic levels. The shaded area shows the number of COVID-19 test claims coming into clinical labs. XIFIN says COVID-19 test claims make up about 20% of the decline in routine test specimens for those labs performing COVID-19 tests. The Dark Report estimates that the clinical laboratory industry has lost $800 million to $900 million in routine test revenue each week since March 23. Weekly revenue losses will continue at this rate until patients begin visiting their physicians and hospitals again perform elective services. (Chart copyright: XIFIN, Inc.)
Many CLIA-certified community laboratories and hospital labs have the diagnostic instruments and experience to perform rapid molecular tests for COVID-19. But when contacted, they tell us that their suppliers do not ship them even minimal quantities of the COVID-19 kits, the reagents, and the consumables. Thus, they cannot meet the needs of their client physicians. Instead, they watch as these physicians refer COVID-19 tests to the nation’s largest labs. The supply shortage prevents these smaller labs from doing larger numbers of COVID-19 test for the patients in the communities they serve. It also prevents them from earning the revenues from COVID-19 testing that currently helps the nation’s “have” labs offset the decline in revenue from routine testing.
Congress, national healthcare policymakers, and state governors need to immediately address this situation. Each week that passes during the COVID-19 pandemic and the shelter-in-place directives drains another $800 million to $900 million in revenue from routine lab testing that previously flowed into the nation’s clinical laboratories.
‘Have-not’ Clinical Labs in Small Towns Will Quietly Shrink and Disappear
Without timely intervention and financial support, the nation’s network of ‘have not’ labs, which have so capably served towns away from big metropolitan centers and rural areas, will quietly begin shrinking. One at a time, labs in small towns will close or sell. Local lab facilities will be shuttered and specimens from small-town patients will be transported to big labs hundreds or thousands of miles away.
It is also true that the financial disaster besetting the nation’s clinical laboratory industry will have comparable dramatic consequences for the in vitro diagnostics (IVD) manufacturers that sell them automation, analyzers, reagents, and other supplies. Since early March, IVD manufacturers watched as the pandemic caused orders for new instruments to collapse. During these same weeks, their clinical lab customers ceased ordering routine test kits at pre-pandemic levels. Dark Daily will cover the challenges confronting the IVD and other diagnostics industries in future e-briefings.
Announcing Free COVID-19 STAT Intelligence Briefings for Clinical Labs
With the COVID-19 pandemic creating chaos in nearly every aspect of healthcare, business, and society, clinical labs and their suppliers need timely intelligence and analysis about the innovations and successes achieved by their peers. This week, Dark Daily and The Dark Report are launching COVID-19 STAT Intelligence Briefings (Copy and paste this URL into your browser: https://www.covid19briefings.com). This comprehensive service is free and will cover four basic areas of needs for clinical laboratories as they ramp up COVID-19 testing:
Daily and weekly COVID-19 testing dashboards to guide every lab’s short-term planning;
Proven steps for labs to introduce and validate COVID-19 tests (both rapid molecular tests and serology tests);
Getting paid for COVID-19 testing to ensure every lab’s financial stability and clinical quality; and
Legal and regulatory updates for labs doing COVID19 tests to ensure full compliance.
Also, to help clinical laboratory leaders deal with the coming wave of COVID-19 serology tests, we are producing a free webinar led by James O. Westgard, PhD, FACB, and Sten Westgard, Director of Client Services and Technology, of Westgard QC, Inc.
Each week that the SARS-CoV-2 pandemic continues, and strict shelter-in-place directives are in place, the clinical laboratory industry loses another almost $900 million in revenue from lower volumes of routine testing. No industry can survive when its incoming revenue collapses by 50% to 60% for sustained periods of time.
Will Congress Recognize the Need for a Financial Rescue of ‘Have-not’ Labs?
Thus, it is incumbent on Congress, elected officials, and healthcare policymakers to recognize the financial consequences of the pandemic to the nation’s clinical laboratories. That is particularly true of the ‘have-not’ clinical labs. They do not have the same access to decisionmakers in government as billion-dollar lab companies.
And yet, these labs located in small communities and rural areas often are the only local labs that can do STAT testing in a couple of hours, and where clinical pathologists are personally familiar with local physicians and patients.
These “have-not” labs are vital healthcare resources. They should receive the help they need to get through this unprecedented crisis that is the COVID-19 pandemic.
How medical laboratories can show value through process improvement methods and analytics will be among many key topics presented at the upcoming Lab Quality Confab conference
Quality management is the clinical laboratory’s best strategy for surviving and thriving in this era of shrinking lab budgets, PAMA price cuts, and value-based payment. In fact, the actions laboratories take in the next few months will set the course for their path to clinical success and financial sustainability in 2020 and beyond.
But how do medical laboratory managers and pathologists address these challenges while demonstrating their lab’s value? One way is through process improvement methods and another is through the use of analytics.
Clinical pathologists, hospital lab leaders, and independent lab executives have told Dark Daily that the trends demanding their focus include:
Ensuring needed resources and appropriate tests,
while the lab is scrutinized by insurance companies and internally by hospital
administration;
“Our impact on patient care, in many cases, is very
indirect. So, it is difficult to point to outcomes that occur. We know things
we do matter and change patient care, but objectively showing that is a real
struggle. And we are being asked to do more than we ever had before, and those
are the two big things that keep me up at night these days,” he added.
This is where process improvement methods and analytics are
helping clinical laboratories understand critical issues and find opportunities
for positive change.
“You need to have a strategy that you can adapt to a changing landscape in healthcare. You have to use analytics to guide your progress and measure your success,” Patricia Nortmann, System Director of Laboratory Services at St. Elizabeth Healthcare, Erlanger, Ky., told Dark Daily.
Clinical Laboratories Can Collaborate Instead of Compete
Prior to a joint venture with TriHealth in Cincinnati, St. Elizabeth lab leaders used data to inform their decision-making. Over about 12 years preceding the consolidation of labs they:
Implemented front-end automation outside the core area and in the microbiology lab.
“We are now considered a regional reference lab in the state
of Kentucky for two healthcare organizations—St. Elizabeth and TriHealth,”
Nortmann said.
Thanks to these changes, the lab more than doubled its
workload, growing from 2.1 million to 4.3 million outreach tests in the core
laboratory, she added.
Christopher Doern, PhD (left), Director of Microbiology and Associate Professor of Pathology at Virginia Commonwealth University Health System; Patricia Nortmann (center), System Director of Laboratory Services at St. Elizabeth Healthcare; and Joseph Cugini (right), Manager Client Solutions at Health Network Laboratories, will present practical solutions and case studies in quality improvement and analytics for clinical laboratory professionals at the 13th Annual Lab Quality Confab, October 15-16, 2019, at the Hyatt Regency in Atlanta, Ga. (Photo copyright: The Dark Report.)
Using Analytics to Test the Tests
Clinical laboratories also are using analytics and information technology (IT) to improve test utilization.
At VCH Health, Doern said an analytics solution interfaces
with their LIS, providing insights into test orders and informing decisions
about workflow. “I use this analytics system in different ways to answer
different questions, such as:
How are clinicians using our tests?
When do things come to the lab?
When should we be working on them?
“This is important for microbiology, which is a very delayed
discipline because of the incubation and growth required for the tests we do,”
he said.
Using analytics, the lab solved an issue with Clostridium
difficile (C diff) testing turnaround-time (TAT) after associating it with
specimen transportation.
Inappropriate or duplicate testing also
can be revealed through analytics. A physician may reconsider a test after discovering
another doctor recently ordered the same test. And the technology can guide
doctors in choosing tests in areas where the related diseases are obscure, such
as serology.
Avoiding Duplicate Records While
Improving Payment
Another example of process
improvement is Health Network Laboratories (HNL) in Allentown, Pa. A team there established an enterprise master patient index (EMPI) and implemented digital tools to find and eliminate
duplicate patient information and improve lab financial indicators.
“The system uses trusted sources of data to make sure data is clean and the lab has what it needs to send out a proper bill. That is necessary on the reimbursement side—from private insurance companies especially—to prevent denials,” Joseph Cugini, HNL’s Manager Client Solutions, told Dark Daily.
HNL reduced duplicate records in its database from 23% to
under one percent. “When you are talking about several million records, that is
quite a significant improvement,” he said.
Processes have improved not only on the billing side, but in
HNL’s patient service centers as well, he added. Staff there easily find
patients’ electronic test orders, and the flow of consumers through their
visits is enhanced.
Learn More at Lab Quality Confab Conference
Cugini, Doern, and Nortmann will speak on these topics and more during the 13th Annual Lab Quality Confab (LQC), October 15-16, 2019, at the Hyatt Regency in Atlanta, Ga. They will offer insights, practical knowledge, and case studies involving Lean, Six Sigma, and other process improvement methods during this important 2-day conference, a Dark Dailynews release notes.
Register for LQC, which is produced by Dark Daily’s sister publication The Dark Report, online at https://www.labqualityconfab.com/register, or by calling 512-264-7103.
As PAMA brings estimated Medicare reimbursement cuts of up to 30% over the next three years to a range of typically high-volume tests and diagnostics, medical laboratories that wish to stay competitive must understand the needs of managed care payers and learn how to optimize collections, reduce denials, and communicate value effectively or risk their financial health
Recent years have seen major shifts in consolidation, automation, and efficiency analysis to help streamline both workflows and cashflows. However, the threat from the current and coming cuts to Medicare lab test prices will be particularly acute for smaller independent laboratories and hospital/health system lab outreach programs. These labs will continue to feel added strain due to reduced reimbursement across 25 of the most common tests billed to Medicare.
And, that doesn’t account for subsequent cuts, which are estimated to reach nearly 30% over the next three years.
Cost of Service Disparities/In-Network Status Further Impact Clinical Labs
If the CLFS reductions weren’t enough, labs face another threat—managed care and commercial payers aligning with big national laboratories and narrowing networks in an attempt to lower costs and provide maximum return for both patients and shareholders. For smaller and independent laboratories, this represents a double threat.
In the first situation, larger laboratories can offer services at lower costs due to increased automation, batch processing, and other scale advantages. This means that while the lower CLFS rates will impact the financial integrity of larger labs, the actual margin lost is less than that of smaller laboratories and facilities that face higher costs to perform tests and provide services.
Compounding the situation, commercial and managed care payers searching out the best value for their patients and shareholders tend to narrow their networks by excluding many independent clinical lab companies and hospital lab outreach programs, amplifying this inherent disparity and skewing the advantage away from independent providers yet again.
Higher cost providers without a clear understanding of promoting their value to payers could have trouble obtaining in-network status. Yet, failing to obtain in-network status may reduce overall test quantities, further raise prices, and make smaller labs less competitive with larger national laboratories—a dangerous cycle with today’s competitive laboratory landscape.
Shifting Focus and Optimizing Managed Care Reimbursements
As the financial stability of Medicare reimbursements wanes, it is imperative that laboratories look to new methods to further increase efficiency and stabilize cashflows. Once a smaller portion of laboratory revenue, managed care organizations and commercial payers will be of increased importance as overall reimbursement rates continue to shrink in the face of healthcare reform and value-based care.
Special June 26 Webinar: Improving Managed Care Reimbursement Efficiency
Understanding not just what these payers are attempting to achieve for their organization—but also how they structure requirements and processes to support their goals—is an essential element of succeeding in this previously smaller share of the marketplace.
For those interested in learning more about critical concerns regarding managed care payers in the post-2018 CLFS landscape, Pathology Webinars is hosting a 90-minute webinar on Tuesday, June 26, 2018, at 2:00 PM Eastern.
The webinar will include presentations from two experts on a range of topics including:
Actionable steps to absorb the loss of Medicare revenue due to the impact of the 2018 CLFS reductions;
How managed care payers process network status and payments;
Who in the managed care chain of command should receive your value proposition;
How to better align your value propositions, policies, and workflows with the requirements of managed care and commercial payers; and,
Understanding the roles managed care payers expect clinical laboratories and anatomic pathologists to play in managing and reducing unnecessary testing.
The first speaker, Frank Dookie, MBA, will provide an inside look at:
How managed care payers function;
Their requirements and workflows; and,
What they look for when considering network status for a laboratory.
Dookie is a laboratory professional who has worked on the payer side for 28 years. He is passionate about the role that diagnostics play or can play in healthcare, and has spent his career working for instrumentation providers, clinical laboratories, the intermediary space between laboratories and managed care companies, and managed care companies.
The second speaker, Michael Snyder, will bring the entire payment process into sharp focus. He will cover:
Optimizing the collection process;
Identifying the purpose of each step, each review, and each team member involved; and,
Critical points laboratories must address to ensure payment.
Snyder is the Senior Vice President of Network Operations for Avalon Healthcare Solutions, LLC, a firm that provides comprehensive benefit management services to the health plan industry and has more than 30 years’ experience in clinical laboratory management.
Frank R. Dookie, MBA (left), Contracting Executive with a major managed care company in Woodbridge, N.J.; and Michael Snyder (right), Senior Vice President with Avalon Healthcare Solutions in Flemington, N.J., will provide critical insights and actionable details for clinical laboratory and anatomic pathology group leaders who want to ensure future revenues.
An Essential Opportunity to Improve Your Reimbursements
This critical webinar offers anatomic pathology groups and medical laboratory managers essential information and actionable next steps to immediately leverage the potential of managed care payers. Additionally, it provides insider insight to laboratories straining to retain financial integrity as reduced reimbursements and increased regulatory burdens strain budgets and cashflows.
To register for the webinar and see further details about discussion topics, use this link (or copy and paste the URL into your browser: https://pathologywebinars.com/current/managed-care-an-insiders-guide-to-improving-your-reimbursement-efficiency-with-strategies-that-work-626/).
As further Medicare payment reductions over the next three years drive reimbursements even lower, understanding how to capture the positive attention of payers—while working within the rules and policies driving their reimbursement decisions—will be an essential element of successful laboratory management and growth. Register now!